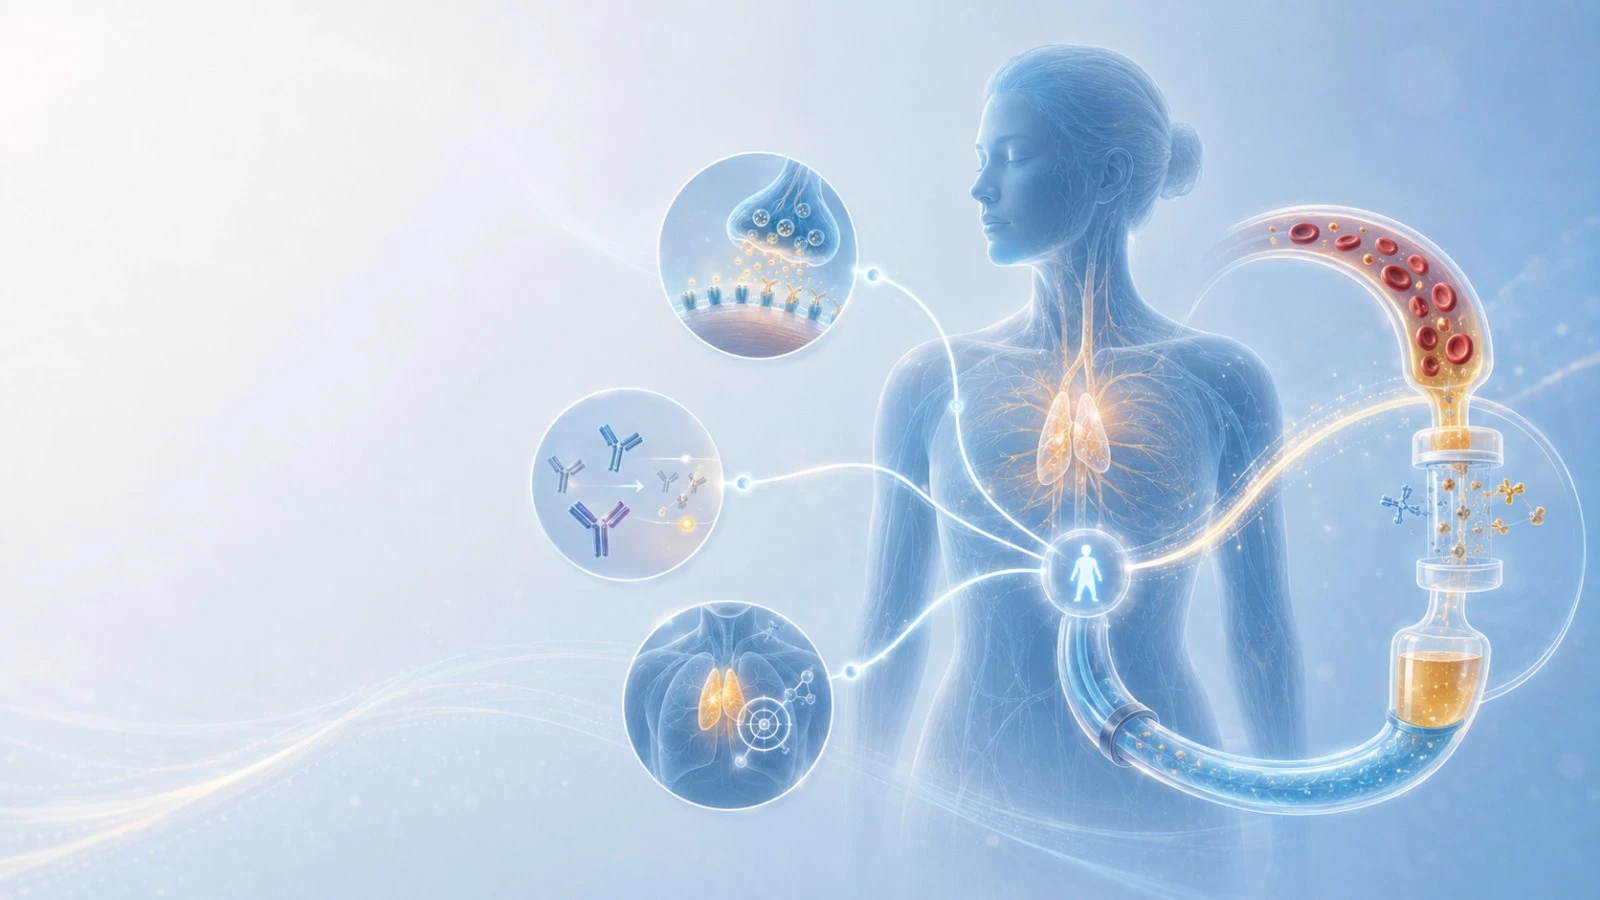
Myasthenia gravis is a chronic autoimmune disease that disrupts communication between the nervous system and skeletal muscles, causing weakness that worsens with activity and improves with rest. It is the most common primary disorder of the neuromuscular junction and one of the most well-understood autoimmune diseases in neurology. While there is no cure, myasthenia gravis is highly treatable, and with appropriate management the majority of people with the condition maintain a normal or near-normal life expectancy.
What Is Myasthenia Gravis?
Myasthenia Gravis Definition
The name comes from Greek and Latin roots: mys (muscle), asthenes (weak), and the Latin gravis (severe). Literally: severe muscle weakness. That etymology is an accurate description. Myasthenia gravis (MG) is a condition in which the immune system produces proteins called antibodies that attack the connection point between nerves and muscles. The result is muscle weakness that accumulates with repeated use and partially recovers with rest.
Unlike many autoimmune diseases that affect organs or connective tissue broadly, MG targets a single, well-defined location in the body. That specificity is part of why MG has been so extensively studied and why neurologists can often use diagnosis-specific treatment strategies.
Myasthenia gravis is sometimes confused with multiple sclerosis (MS), another autoimmune condition that causes weakness and fatigue. The two are distinct diseases. MS involves damage to the protective coating around nerve fibers in the brain and spinal cord. MG involves disruption at the point where nerves connect to muscles – the brain and spinal cord are not affected. The symptoms can look similar from the outside, but the underlying biology, diagnosis, and treatment are entirely different.
How the Neuromuscular Junction Is Affected

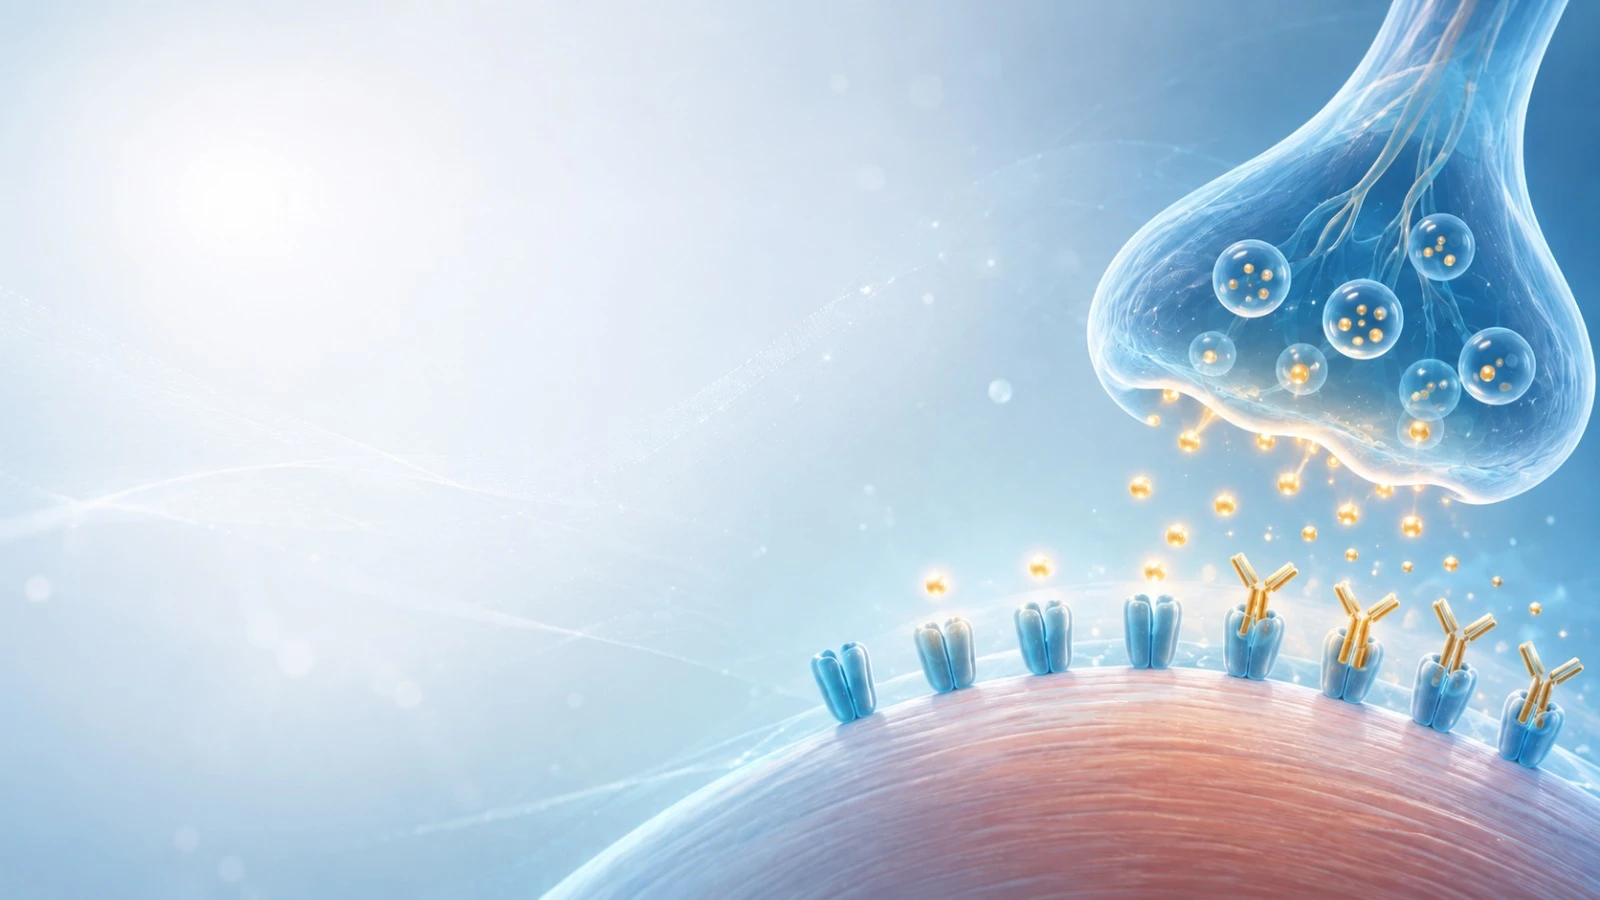
In MG, antibodies block acetylcholine receptors at the neuromuscular junction, weakening the nerve-to-muscle signal.
To understand MG, it helps to understand what normally happens when you decide to move a muscle. A nerve sends a signal down to the point where it meets the muscle – a tiny gap called the neuromuscular junction. At that junction, the nerve releases a chemical messenger called acetylcholine, which crosses the gap and attaches to receptors on the muscle. That attachment triggers the muscle to contract.
In myasthenia gravis, the immune system produces antibodies that attack those receptors. With fewer working receptors available, the muscle receives a weaker signal. It contracts unreliably, and under sustained use the signal degrades further – which is why MG weakness tends to build throughout activity and improve with rest. Holding the arms overhead, chewing through a meal, or keeping the eyes focused at the end of the day are classic scenarios where this failure becomes noticeable.
In most patients, these antibodies target the acetylcholine receptor (AChR) directly. In a smaller group, they target a related protein called MuSK, which helps keep receptors organized and functional at the junction. The specific antibody type matters for how MG presents and how it responds to treatment.
What Causes Myasthenia Gravis?
Is Myasthenia Gravis an Autoimmune Disease?
Yes. MG is a classic autoimmune disease. The immune system, designed to attack foreign threats like bacteria and viruses, misidentifies proteins at the neuromuscular junction and produces antibodies against them. AChR antibodies are found in approximately 85 percent of patients with generalized muscle weakness and in roughly 50 percent of those with involvement limited to the eyes.
The precise trigger for this immune malfunction varies and in many cases is never fully identified. Known contributing factors include abnormalities of the thymus gland, genetic predisposition, and in some cases preceding infections or immune-activating events.
Is Myasthenia Gravis Hereditary?
MG is not a directly inherited disease. Most cases are acquired during a person’s lifetime rather than passed down through families. However, genetic susceptibility plays a role. Specific immune-related gene variants are associated with increased risk of MG and other autoimmune conditions, and relatives of people with MG have a higher rate of autoimmune disease in general. Having a family history of autoimmune conditions increases risk, but MG itself does not follow a predictable inheritance pattern.
It is worth noting that a separate condition called congenital myasthenic syndrome involves inherited genetic mutations affecting the neuromuscular junction. This is distinct from autoimmune MG and is not discussed on this page.
The Role of the Thymus in Myasthenia Gravis
The thymus gland, located in the chest behind the sternum, plays a central role in immune development. It is where certain immune cells mature and learn to distinguish the body’s own proteins from foreign ones. In MG, that process goes wrong.
In many adults with myasthenia gravis, the thymus remains enlarged or abnormal when it should have shrunk after puberty. Approximately 10 to 15 percent of people with MG have a thymoma – a tumor of the thymus – and many others, especially in certain MG subtypes, have thymic hyperplasia or other thymic abnormalities. These thymic abnormalities may contribute to the immune activity involved in MG. This is why thymectomy may be considered in select patients. For some, it can reduce symptom burden or the need for medication over time, depending on MG subtype, age, antibody status, and the presence or absence of thymoma.
What Can Trigger or Worsen Myasthenia Gravis?
While the root cause of MG is immune dysfunction, many patients find that specific factors reliably provoke flares or worsen existing weakness. Common triggers include physical overexertion, emotional stress, illness or infection, extreme heat, and insufficient sleep. Certain medications – including some antibiotics, beta blockers, and magnesium-containing compounds – are known to interfere with neuromuscular transmission and can worsen MG symptoms in some patients. Identifying personal triggers is an important part of day-to-day management and should be discussed with a treating physician early in the course of the disease.
Types of Myasthenia Gravis
MG is not a single uniform condition. Classification by antibody type, the muscle groups involved, and the extent of disease has important implications for diagnosis, prognosis, and treatment selection.
Generalized Myasthenia Gravis
Generalized MG is the most common form. Weakness is not limited to the eyes but affects the limbs, neck, facial muscles, and in more severe cases the muscles controlling speech and swallowing and the respiratory muscles. Many patients who initially present with eye symptoms progress to generalized MG within two to three years of onset. Some patients also report fatigue, reduced stamina, or cognitive fog. These experiences are important to discuss with a clinician, even though MG is primarily defined by muscle weakness at the neuromuscular junction rather than direct involvement of the brain or spinal cord.
Ocular Myasthenia Gravis
In ocular MG, weakness is confined to the muscles controlling eye movement and eyelid position. Drooping of one or both eyelids and double vision are the characteristic findings. For some patients, the condition remains ocular and does not progress to generalized involvement. Ocular MG may respond differently than generalized MG, and early evaluation and appropriate management may help clarify risk and guide treatment decisions.
Bulbar Myasthenia Gravis
Bulbar MG refers to predominant involvement of the muscles governing speech, chewing, and swallowing. Patients may experience a nasal quality to speech, difficulty eating, or choking on liquids. Bulbar involvement carries particular clinical significance because it can compromise airway protection and nutritional status, and may signal an increased risk of respiratory crisis.
Seronegative Myasthenia Gravis
Roughly 10 to 15 percent of MG patients test negative for AChR antibodies on standard blood panels. Some of these patients carry MuSK or LRP4 antibodies that require additional testing to detect. Those with no identifiable antibody are classified as seronegative MG. The clinical picture is similar to antibody-positive disease, but seronegative cases – particularly those involving MuSK antibodies – can differ in where weakness appears, how the thymus is involved, and how the disease responds to treatment. Diagnosis in these cases relies more heavily on clinical examination and nerve testing.
Thymoma-Associated Myasthenia Gravis
Thymoma-associated MG describes cases where a thymoma is identified alongside the diagnosis. Approximately 10 to 20 percent of people with MG are reported to have a thymoma, with estimates varying by population and study. Thymoma-associated MG often presents with more severe generalized weakness and has a higher rate of AChR antibody positivity. Identifying a thymoma is clinically important because these tumors carry their own implications that require management independent of MG.
How Common Is Myasthenia Gravis?
MG is classified as a rare disease but is the most prevalent primary neuromuscular junction disorder. According to a 2024 claims-based analysis, the diagnosed prevalence of MG in the United States in 2021 was approximately 37 per 100,000 people, with roughly 75,000 to 100,000 Americans currently living with the condition. Prevalence and incidence figures have been rising; a trend researchers attribute largely to improved disease awareness and better diagnostic tools rather than a true increase in underlying cases. MG is more common in women under 40 and men over 60, though it can develop at any age.
Myasthenia Gravis Prognosis and Life Expectancy
Is Myasthenia Gravis Fatal?
MG is not typically fatal with modern management. With modern diagnosis, specialty care, and emergency support, most people with MG have a normal or near-normal life expectancy. The primary life-threatening complication is myasthenic crisis – an acute deterioration in which respiratory muscle weakness can lead to breathing failure requiring emergency intervention. Outcomes during myasthenic crisis have improved dramatically with modern critical care, but any signs of breathing difficulty, severe swallowing problems, or rapidly worsening weakness should be treated as a medical emergency.
MG does not have a defined end stage in the way that some progressive neurological diseases do. The term “end-stage MG” is not a recognized clinical classification. Severity fluctuates significantly over time, and outcomes are heavily influenced by treatment approach.
Is Myasthenia Gravis Progressive?
MG does not follow a predictable progressive course. Symptoms typically reach peak severity within one to three years of onset, after which the course is variable. About 20 percent of patients may experience remission at some point, meaning symptoms become minimal or absent for a period of time, though remission is not always permanent. Spontaneous remission – where symptoms ease significantly without a change in treatment – does occur, though it is unpredictable. The more consistent path to sustained low disease activity is timely evaluation and individualized treatment that considers symptom control, immune activity, trigger management, and each patient’s overall health.
Most people with myasthenia gravis live to an average life expectancy. The degree to which MG affects quality of life is heavily shaped by how proactively and appropriately it is treated.
Frequently Asked Questions About Myasthenia Gravis
Is myasthenia gravis the same as multiple sclerosis?
No. Myasthenia gravis and multiple sclerosis are two separate autoimmune diseases that can produce some overlapping symptoms – weakness, fatigue, and vision changes – but they affect entirely different parts of the nervous system. MS damages the protective sheath around nerve fibers in the brain and spinal cord. MG disrupts the junction between peripheral nerves and muscles. They have different diagnostic tests, different treatments, and different disease courses. A confirmed diagnosis of one does not indicate the presence of the other.
Can myasthenia gravis go away on its own?
For some patients, yes. Spontaneous remission – a significant reduction or disappearance of symptoms without a change in treatment – does occur in MG, though it cannot be reliably predicted or induced. Roughly 20 percent of patients experience remission at some point, and some experience sustained periods of minimal symptoms lasting many years. That said, MG is a chronic condition and most patients require ongoing management. The likelihood of achieving and maintaining low disease activity is generally improved with appropriate medical care, careful monitoring, and an individualized plan that considers both symptom control and the immune activity involved in the disease.
Is myasthenia gravis hereditary?
Myasthenia gravis is not a directly inherited disease. It does not follow a family inheritance pattern the way conditions like cystic fibrosis or Huntington\’s disease do. Most cases arise spontaneously. However, genetic factors do influence susceptibility – people with certain immune-related gene variants are more prone to autoimmune conditions generally, and MG does occur more frequently in families with a history of other autoimmune diseases. Having a first-degree relative with an autoimmune condition modestly increases risk but does not mean MG will develop.
What triggers a myasthenia gravis flare-up?
MG symptoms can worsen significantly in response to specific triggers, even when the disease is otherwise well-controlled. The most commonly reported include physical overexertion, emotional or psychological stress, infections and illness, extreme heat or fever, and disrupted sleep. Certain medications are also known to interfere with neuromuscular transmission in some patients – these include some antibiotics, cardiovascular drugs, and magnesium-based compounds. Patients newly diagnosed with MG should receive a list of medications to use with caution and should discuss personal trigger patterns with their physician as part of building an ongoing management plan.
What is the life expectancy for someone with myasthenia gravis?
For most people with MG, life expectancy is not significantly reduced compared to the general population. This is a meaningful change from historical outcomes, when MG was far more dangerous before modern treatment and critical care were available. Today, the main serious risk is myasthenic crisis rather than the disease itself progressing to a fatal stage. Most people with MG are able to work, maintain active lives, and manage the condition long-term with appropriate care. Prognosis is best when the disease is identified early and care is coordinated with clinicians experienced in MG, including attention to symptom control, immune activity, medication safety, flare prevention, and overall health.
Understanding Your Options
A myasthenia gravis diagnosis raises immediate questions about what management looks like over the long term. Standard treatment may include medications for symptom control, immune-directed therapies, thymectomy in select patients, IVIG, plasmapheresis, and emergency support when needed. For those who are not achieving adequate control, or who want to understand the full landscape of available options, the next step is understanding what treatment actually involves and how each option may fit into an individualized care plan.
Treatment options for myasthenia gravis – including conventional medications, thymectomy, IVIG, plasmapheresis, and MaxWell Clinic’s integrative Habitat Optimizing Plasma Exchange® (H.O.P.E.) approach to immune and whole-body support – are covered in detail on our myasthenia gravis treatment page.