Myasthenia gravis treatment is not one-size-fits-all. The right plan depends on MG subtype, antibody status, thymus findings, symptom severity, treatment response, and guidance from a neuromuscular specialist. This page covers first-line medications, thymectomy, IVIG, plasmapheresis, emerging therapies, and MaxWell Clinic’s integrative Habitat Optimizing Plasma Exchange® (H.O.P.E.) approach.
Medically reviewed by David Haase, MD, Founder of MaxWell Clinic.
Is Myasthenia Gravis Treatable?

Myasthenia gravis treatment options are individualized. H.O.P.E. is discussed as an adjunct to neurologist-directed care.
Yes. MG is not considered curable in the conventional sense, but it is treatable. Many patients improve with appropriate care, and some achieve periods of minimal symptoms or remission. Outcomes vary based on disease subtype, antibody status, thymus involvement, overall health, and response to treatment. Some therapies focus on improving nerve-to-muscle signaling, while others affect immune activity or reduce circulating antibodies. The goal is to reduce disease burden while minimizing treatment risk, but the right approach should be individualized and medically supervised.
Treatment Goals: Remission vs. Symptom Control
Treatment goals vary by patient. For some, the immediate goal is safer swallowing, stronger breathing, or better daily function. For others, the goal may be fewer flares, less medication burden, or sustained low disease activity. Remission may be possible for some patients, but it is not guaranteed. The path looks different depending on disease type, antibody status, thymus involvement, and response to care. Patients who feel they have only been offered symptom management may benefit from a broader conversation with a neuromuscular specialist about available options.
First-Line Myasthenia Gravis Medications
Acetylcholinesterase Inhibitors
The first medication most MG patients are prescribed is pyridostigmine (Mestinon). It works by slowing the breakdown of acetylcholine at the neuromuscular junction, giving the available receptors more exposure to the chemical signal that triggers muscle contraction. Pyridostigmine improves functional strength in most patients and takes effect within 30 to 60 minutes of a dose. It does not treat the underlying immune dysfunction – it compensates for it. For mild MG, it may be sufficient on its own. For moderate to severe disease, it is typically a starting point, not a destination.
Corticosteroids and Immunosuppressants
When pyridostigmine alone is not adequate, immunosuppressive therapy is added. Prednisone is the most commonly used corticosteroid and can produce significant improvement in MG symptoms, though it often causes an initial temporary worsening before improvement begins. Long-term corticosteroid use carries well-known risks including bone loss, weight gain, metabolic effects, and increased infection susceptibility.
Steroid-sparing immunosuppressants – including azathioprine, mycophenolate mofetil, and tacrolimus – are added to allow prednisone doses to be reduced over time. These drugs suppress the immune system broadly and can take months to reach full effect. They require ongoing monitoring for side effects including liver toxicity and increased infection and cancer risk with long-term use.
Medications to Use With Caution in Myasthenia Gravis
Certain medications may worsen MG symptoms in some patients by interfering with neuromuscular transmission or immune stability. These may include certain antibiotics, beta blockers, calcium channel blockers, magnesium-containing compounds, and some anesthetic agents. This does not mean every medication on a caution list is automatically forbidden, but patients with MG should tell every medical and dental provider about their diagnosis and review new medications with their physician or pharmacist. This is an ongoing responsibility throughout the disease course, not only at initial diagnosis.
Myasthenia Gravis Surgery: Thymectomy
Thymectomy, surgical removal of the thymus, is an established treatment consideration for selected MG patients, especially those with thymoma and certain patients with generalized AChR-positive MG. In appropriate candidates, thymectomy may improve clinical outcomes and reduce the need for immunotherapy over time. It is not appropriate for every patient, and decisions should be made with a neuromuscular specialist and thoracic surgeon.
Research on thymectomy shows that some appropriately selected patients experience meaningful improvement, and some achieve remission or reduced medication needs over time. Outcomes vary by age, antibody status, thymus findings, disease duration, surgical approach, and other individual factors. Minimally invasive and robotic approaches may reduce recovery burden in some settings, but the specific surgical plan should be guided by an experienced thoracic surgery team.
Seronegative MG and late-onset MG can have variable responses to thymus removal, and the decision requires careful evaluation of individual disease characteristics. Thymectomy is a one-time intervention, not a chronic treatment, and any immune-related benefits may continue to develop gradually after surgery.
Advanced and Rapid-Acting Myasthenia Gravis Treatments
IVIG for Myasthenia Gravis
Intravenous immunoglobulin (IVIG) is an infusion therapy derived from pooled human plasma. In MG, it works by modulating the immune response and interfering with pathogenic antibody activity at the neuromuscular junction. IVIG is used primarily in two contexts: acute treatment during myasthenic crisis and as a bridge therapy when other treatments need time to take effect. It can also be used on a maintenance basis in patients who do not tolerate or respond adequately to standard immunosuppressants. Effects typically begin within days and last several weeks.
Plasmapheresis for Myasthenia Gravis
Plasmapheresis, also called plasma exchange, is a procedure that removes plasma from the blood, filters out circulating antibodies and other plasma components, and returns replacement fluid to the body. In MG, plasma exchange can produce relatively rapid improvement in some patients because it directly reduces circulating antibody burden. It is often used in urgent settings, before surgery, during significant worsening, or as a bridge while longer-term therapies take effect.
As the Myasthenia Gravis Foundation of America explains, repeated plasma exchange treatments may be needed because the body continues producing antibodies. For that reason, conventional plasma exchange is often used as part of a broader care plan rather than as a standalone long-term strategy.
Can Myasthenia Gravis Improve Over Time?
Some people with MG experience major improvement, sustained low disease activity, or remission. However, MG is not considered cured simply because symptoms improve. Treatments that reduce antibody burden or influence immune activity may help some patients achieve better control, but results vary and ongoing neurological care remains important. The larger question for many patients is how to support better function, reduce treatment burden when possible, and consider options that fit their disease pattern and medical history.
Habitat Optimizing Plasma Exchange® (H.O.P.E.) at MaxWell Clinic
Therapeutic plasma exchange has been used in MG care for decades, most often in specific clinical settings where rapid antibody reduction is needed. MaxWell Clinic’s H.O.P.E. approach builds on the plasma exchange model with an integrative, individualized framework focused on the patient’s broader biological environment.
Habitat Optimizing Plasma Exchange® (H.O.P.E.) is MaxWell Clinic’s patented, advanced approach to therapeutic plasma exchange. It is not simply a different machine or a different version of the same procedure. It is a broader clinical framework that considers both what is removed from the blood and what is returned to it, based on the patient’s health status, biological markers, and goals.
How H.O.P.E. Differs from Conventional Plasmapheresis
Conventional plasmapheresis generally focuses on what is removed. It can reduce circulating antibodies and inflammatory proteins and may produce relatively rapid clinical improvement in selected situations. However, the immune system may continue producing antibodies after the procedure ends, which is why conventional plasma exchange is often used as a short-term or bridge therapy in MG care.
H.O.P.E. asks a second question: what do we put back in? The replacement solution in H.O.P.E. is personalized based on your health status, biological markers, and specific goals. It may include albumin and other supportive compounds selected by the clinical team to help optimize the patient’s internal environment during the exchange process.
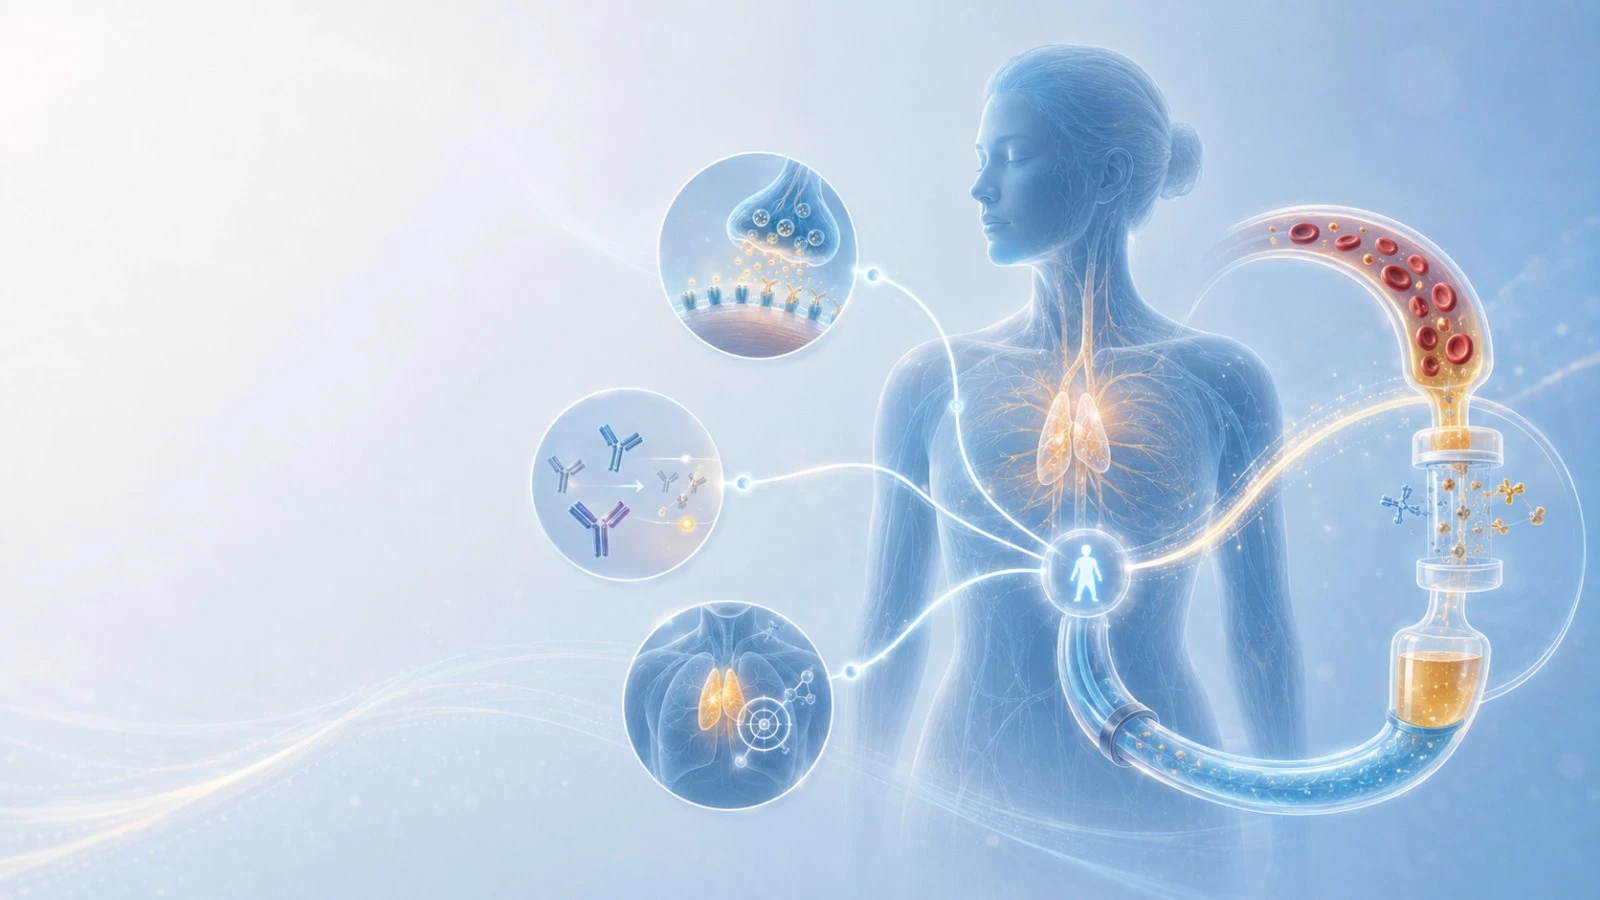
Think of plasma as part of the environment your cells live in. When plasma contains high levels of inflammatory mediators, antibodies, oxidative stress markers, or metabolic waste, the surrounding biological terrain may be less supportive of healthy function. H.O.P.E. is designed to reduce selected circulating burdens and replace plasma with a personalized solution chosen by the clinical team. The procedure follows three steps: Remove, Clean, and Replace and Optimize.
For patients with myasthenia gravis, this matters because the AChR antibodies associated with the disease do not exist in isolation. They are produced by an immune system operating within a broader internal environment. H.O.P.E. is not presented as a cure for MG or a replacement for neurologist-directed care, but it may be considered for selected patients as part of a broader, physician-guided plan.
What Patients Report After H.O.P.E.
Patients undergoing H.O.P.E. for various health concerns have reported improvements in energy, sleep, mental clarity, and overall well-being. These reports are not a guarantee of results and should not be interpreted as proof that H.O.P.E. treats, cures, or reverses MG. For someone with MG, the question is whether this approach is appropriate as part of a broader, physician-guided care plan.
MaxWell Clinic: The Nation’s Largest Private Outpatient Apheresis Center
MaxWell Clinic operates the largest private outpatient apheresis center in the United States. The clinic has performed over 1,000 plasma exchanges and has pioneered H.O.P.E. since 2019, building on more than seven years of clinical expertise. Dr. David Haase, founder of MaxWell Clinic and a leading expert in plasma exchange, regularly teaches clinicians across the country through seminars, webinars, and training programs. MaxWell Clinic receives patient referrals from physicians across the country for advanced plasma exchange.
What to Expect During Treatment
H.O.P.E. is an outpatient procedure. Each session lasts two to four hours and is performed in MaxWell Clinic’s apheresis center. For patients with autoimmune conditions including myasthenia gravis, the H.O.P.E. for Autoimmunity pathway may include clinician visits, a series of H.O.P.E. procedures, IV nutrient support, and pre- and post-testing that may measure immune-cell activity, inflammatory and oxidative stress markers, and microvascular function. The exact plan depends on the patient’s evaluation and clinical needs.
Treatment is closely monitored throughout. Side effects, when they occur, are often mild, such as tingling or temporary blood pressure changes, and are managed in real time by the clinical team. As with any procedure, risks and suitability should be reviewed during consultation before treatment begins.
Who May Be a Candidate
H.O.P.E. for Autoimmunity may be considered for some patients with confirmed autoimmune conditions, including MG, who want to explore an integrative plasma exchange approach alongside their existing neurological care. It may be most relevant for patients who are not achieving adequate control, are concerned about long-term medication burden, have experienced significant side effects, or want a broader evaluation of immune and inflammatory factors.
Candidacy is determined through a consultation with MaxWell Clinic’s clinical team. Because every health journey is unique, the evaluation process is designed to determine whether H.O.P.E. is an appropriate fit before treatment begins and to coordinate with the patient’s medical team when appropriate.
To find out whether H.O.P.E. for Autoimmunity may be an option for your myasthenia gravis, contact MaxWell Clinic at (615) 370-0091 or schedule a consultation online.
New and Emerging Treatments for Myasthenia Gravis
The MG treatment landscape has expanded significantly in recent years. Newer targeted therapies include FcRn blockers, complement inhibitors, and other immune-targeted treatments for specific antibody-positive forms of generalized MG. These therapies can be important options for patients who do not respond adequately to older approaches or who need a more targeted strategy. Patients should discuss eligibility, risks, benefits, cost, and monitoring with a neuromuscular specialist.
These treatments represent genuine progress in conventional MG pharmacology. For patients who are not responding to standard approaches, they offer additional options worth discussing with a neurologist. Like all MG treatments, they work through specific mechanisms and should be evaluated in the context of the patient’s disease subtype, goals, medical history, and overall care plan.
Finding a Myasthenia Gravis Specialist Near You
Managing MG effectively requires a team. A neuromuscular neurologist should be at the center of that team, with subspecialty input as needed for thymus management, respiratory monitoring, and integrative care. For patients in the Nashville and Brentwood area, MaxWell Clinic works alongside existing neurological care to offer the H.O.P.E. protocol as a complement to, not a replacement for conventional neuromuscular management.
If you are not yet connected with a neuromuscular specialist, your primary care physician or general neurologist can provide a referral. Academic medical centers in major metropolitan areas typically have dedicated neuromuscular clinics with experience managing complex MG cases.
To learn whether H.O.P.E. is appropriate for your situation, contact MaxWell Clinic at (615) 370-0091 to schedule an initial consultation.
Frequently Asked Questions About Myasthenia Gravis Treatment
What is the best treatment for myasthenia gravis?
There is no single best treatment. The right approach depends on disease type, antibody status, severity, thymus involvement, individual response, and the patient’s overall health. For many patients, treatment begins with pyridostigmine and may escalate to immunosuppression if symptoms are not adequately controlled. For patients with thymic abnormalities or certain AChR-positive generalized cases, thymectomy may be part of the conversation. For those not achieving adequate control or experiencing significant side effects, advanced options including IVIG, plasma exchange, targeted therapies, and adjunctive integrative approaches may deserve careful evaluation with the appropriate medical team.
Is there a cure for myasthenia gravis?
There is no approved cure for MG. Some patients achieve remission or sustained low disease activity, but this varies. Treatment decisions should be individualized and guided by a neuromuscular specialist. Integrative approaches may support broader health goals, but they should not be presented as a cure or replacement for MG-directed medical care.
How long does myasthenia gravis treatment last?
Most patients with MG require long-term, ongoing management rather than a single defined course of treatment. Medication plans are adjusted based on disease activity, response, side effects, and the patient’s goals. Thymectomy is a one-time intervention whose effects may continue to develop over years. Plasma exchange, in conventional application, is often intermittent or used in specific clinical situations. The H.O.P.E. for Autoimmunity pathway at MaxWell Clinic is structured as a defined course, followed by evaluation and, if needed, a customized continuation plan.
Can myasthenia gravis be treated without steroids?
For some patients, steroid-sparing strategies may be possible. Options may include pyridostigmine, thymectomy in selected candidates, steroid-sparing immunosuppressants, targeted biologic therapies, IVIG, or plasma exchange depending on the case. H.O.P.E. may be discussed as an adjunctive integrative plasma exchange approach, but it should not be positioned as a complete replacement for neurologist-directed MG care. Steroid avoidance or minimization is a legitimate treatment goal and should be part of the conversation with any MG specialist.
What is the difference between IVIG and plasmapheresis for MG?
Both IVIG and plasma exchange are rapid-acting treatments used in similar clinical contexts, such as crisis management, pre-surgical preparation, significant worsening, or bridging to longer-term therapy. The key difference is mechanism: IVIG works by modulating immune activity and interfering with antibody function without directly removing the antibodies themselves, while plasmapheresis directly removes antibodies and other plasma components from circulation. Both can be effective, and the choice depends on patient response, clinical context, availability, risks, and the treating team’s judgment.
The best myasthenia gravis treatment choice depends on patient response, clinical context, availability, risks, and the treating team’s judgment.