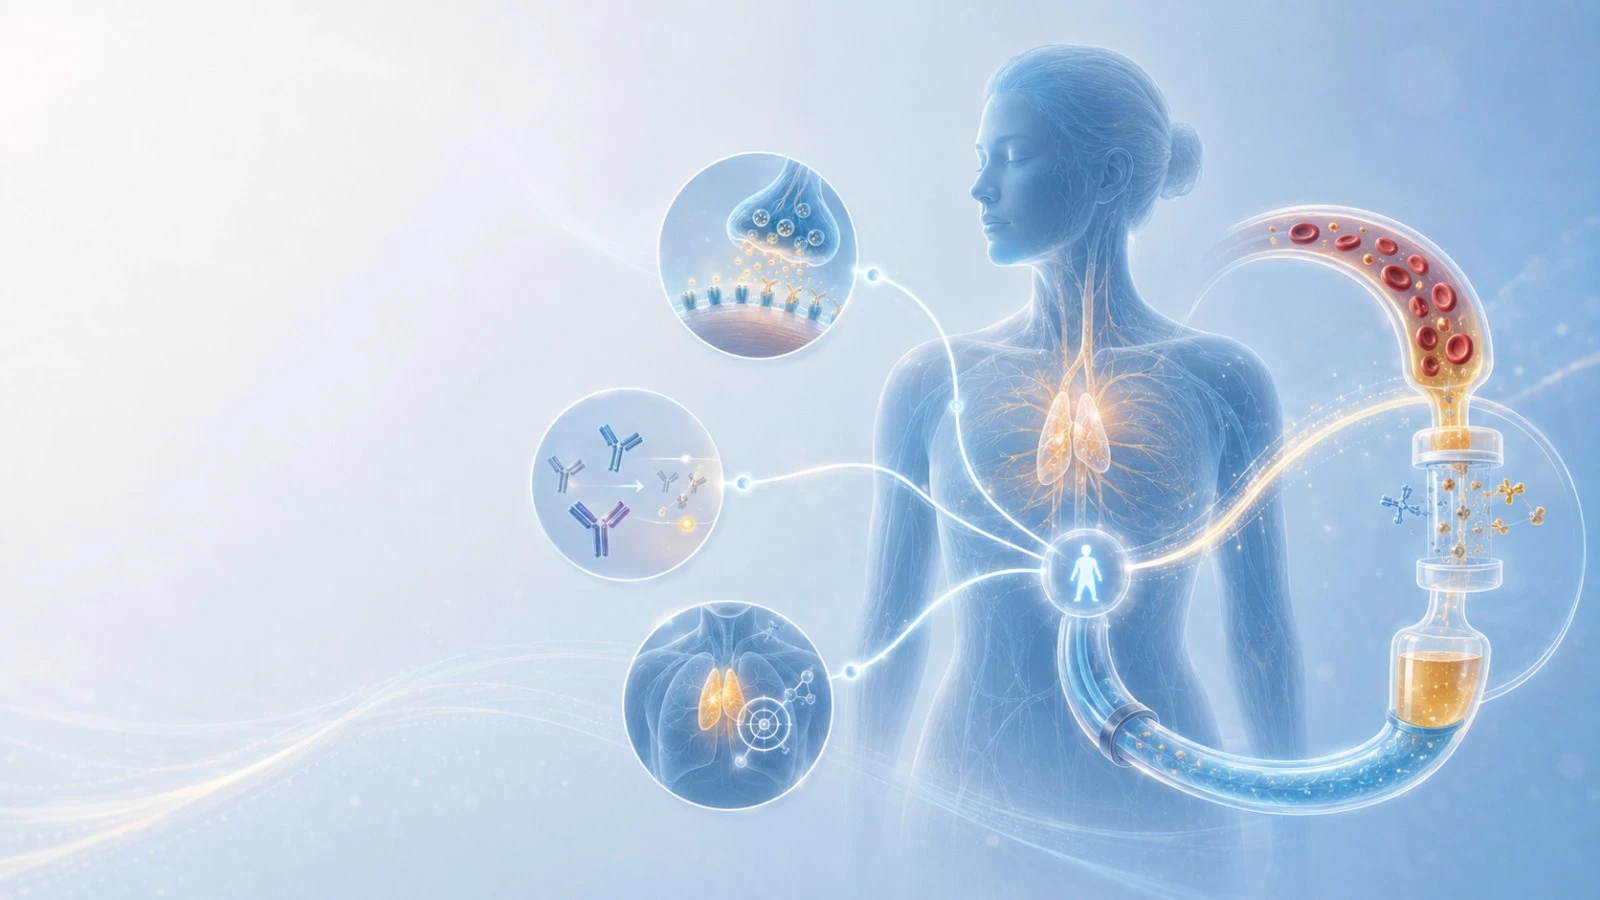
Myasthenia gravis diagnosis usually depends on a neurological examination, antibody blood tests, and electrodiagnostic testing. The process can take time because symptoms fluctuate, overlap with other conditions, and no single test confirms MG in every patient. In one European study of generalized MG, more than one-quarter of patients experienced a diagnostic delay longer than one year. MG may be mistaken for other neurological, eye, thyroid, respiratory, or fatigue-related conditions before the correct diagnosis is identified.
Understanding how MG is diagnosed, and what the testing process actually involves, helps patients advocate for themselves and move through the workup with more confidence.
How Is Myasthenia Gravis Diagnosed?

A typical MG workup moves from clinical exam to antibody testing to electrodiagnostic studies.
No single test confirms MG in every patient. Diagnosis is usually based on the pattern of symptoms, neurological examination, antibody testing, and, when needed, electrodiagnostic studies. A neurologist, ideally one with experience in neuromuscular disease, typically leads the diagnostic workup. In straightforward cases, the process can move quickly. In atypical presentations, particularly when blood tests come back negative, confirming MG requires more specialized testing and a higher level of clinical judgment.
The diagnostic process generally follows a sequence: the physician begins with a clinical examination to look for the characteristic pattern of fatigable weakness, then moves to blood tests to check for known MG antibodies, then to electrodiagnostic testing if the blood work is inconclusive or if the presentation warrants it.
Why Diagnosis Is Often Delayed
Several factors contribute to delayed diagnosis. MG symptoms fluctuate, so patients may appear normal during an office visit. The early symptoms – drooping eyelids, intermittent double vision, mild swallowing changes – are easy to attribute to other causes. When MG is misdiagnosed, it may be mistaken for other neurologic, eye, thyroid, respiratory, or fatigue-related conditions. Eye symptoms are frequently evaluated in ophthalmology before neurology is consulted.
Patients who present with predominantly bulbar symptoms and no eye involvement are particularly prone to delay, as the MG pattern is less immediately recognizable. Seronegative cases – where standard blood tests are negative – add another layer of diagnostic complexity. The key for patients is to ask about a formal neuromuscular evaluation if MG is suspected and initial workup has been unrevealing.
Laboratory Tests for Myasthenia Gravis
Myasthenia Gravis Blood Test: Antibody Panel
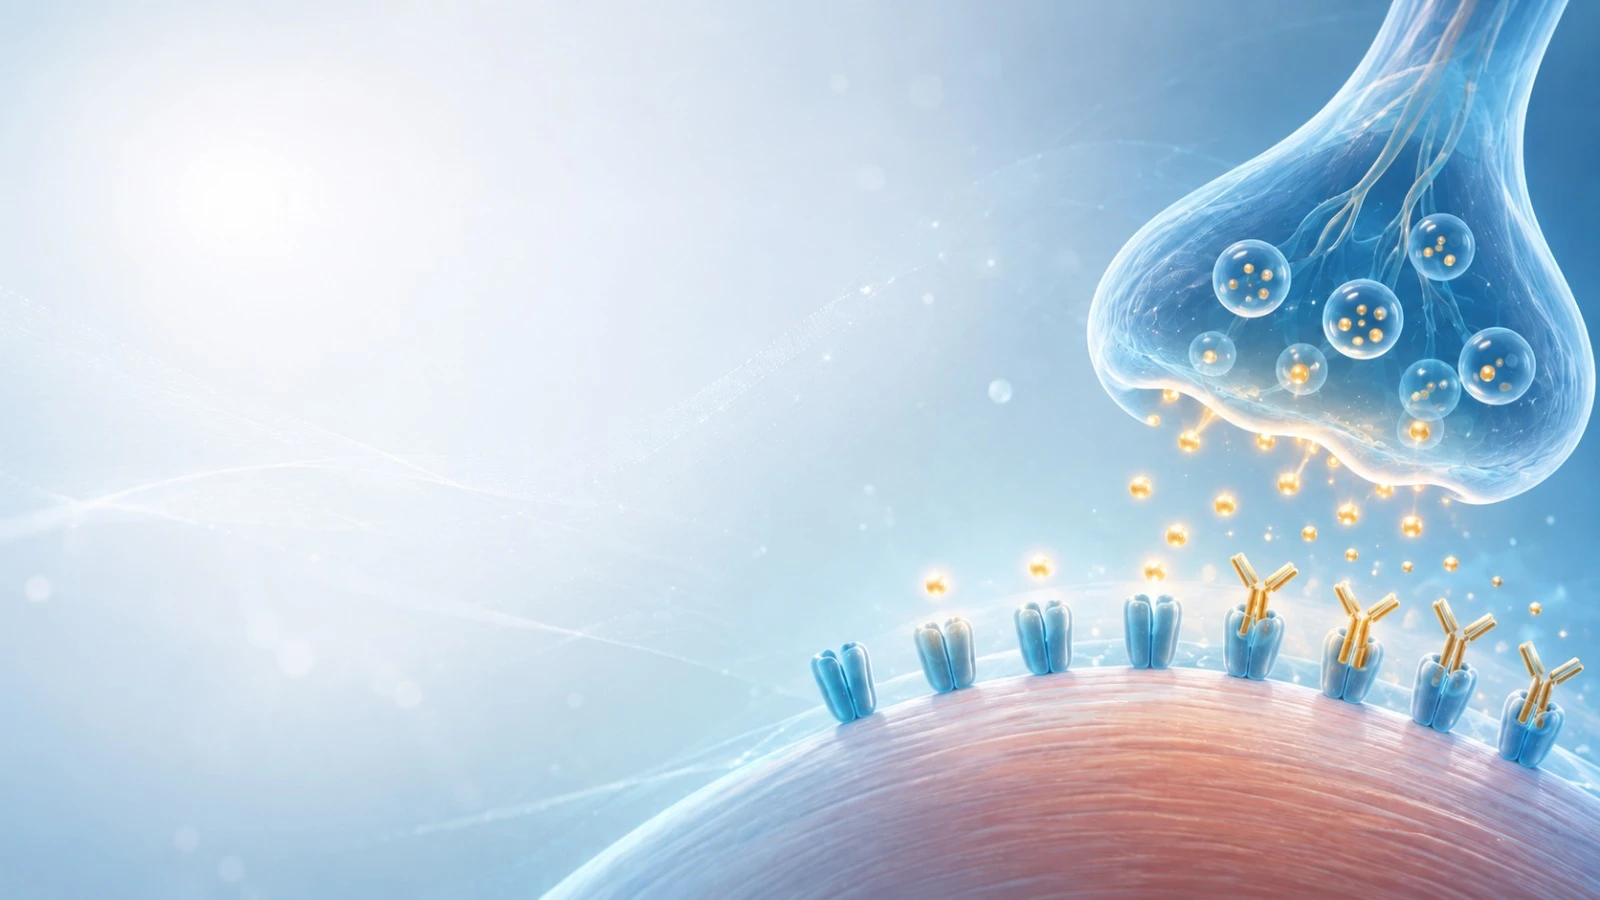
The first step in laboratory testing is usually a blood draw to check for antibodies associated with MG. AChR antibodies are the most common antibodies found in MG, especially in generalized disease. In a patient with characteristic symptoms, a positive AChR antibody result strongly supports the diagnosis of MG and may be enough to confirm the diagnosis in many cases. When AChR testing is negative, clinicians may consider additional testing for MuSK, LRP4, or other antibody patterns depending on the case.
The antibody panel is typically the fastest and most accessible first step, available through standard reference laboratories and most hospital systems.
AChR and Anti-MuSK Antibody Testing
AChR antibodies are the primary target in many MG antibody panels. A negative AChR result does not rule out MG, particularly in ocular or seronegative presentations. Specificity is generally high, so a positive result in the right clinical context is meaningful, but results should always be interpreted alongside the patient’s symptoms and examination findings.
For patients who test negative for AChR antibodies, anti-MuSK antibody testing is often considered next. MuSK-positive MG is less common but clinically important, as it may involve more prominent bulbar weakness and can respond differently to some treatments. A smaller subset of patients carries LRP4 antibodies or other antibody patterns that require more specialized testing to detect.
Seronegative Myasthenia Gravis: When Blood Tests Are Negative
Patients with no detectable antibody on standard panels are classified as seronegative. This does not mean they do not have MG – it means the diagnosis requires more clinical and electrodiagnostic evidence to establish. Seronegative MG is diagnosed based on the clinical pattern, the response to testing, and EMG findings. Management may be similar to seropositive disease, though treatment response can differ by antibody status, disease pattern, and individual patient factors.
Myasthenia Gravis Panel (LabCorp and Quest)
Major reference laboratories, including LabCorp and Quest Diagnostics, offer MG antibody testing, but panels vary in scope. Patients who have been told their MG workup was normal may want to ask their physician which specific antibodies were tested, as not all panels include the same markers or specialized testing methods.
Bedside and Office Tests for Myasthenia Gravis
The Ice Pack Test
The ice pack test is a simple, low-risk bedside assessment sometimes used when ptosis is present. A bag of ice is held over the closed eyelid for a short period, then removed. In MG, cooling may temporarily improve neuromuscular transmission, so eyelid drooping may visibly improve after the ice is removed. A positive result can support suspicion for MG, but it does not replace a complete diagnostic workup.
The Tensilon (Edrophonium) Test
The Tensilon test used edrophonium, a short-acting drug that temporarily boosted acetylcholine at the neuromuscular junction. In MG, this could produce a rapid but brief improvement in muscle strength that was visible to the examiner. The test was historically used to help diagnose MG, but it is used far less often in current practice and edrophonium availability has been significantly limited in the United States in recent years. Most modern evaluations rely instead on antibody testing, bedside assessments, electrodiagnostic testing, and imaging when appropriate.
Confirmatory Testing
Electromyography (EMG) for Myasthenia Gravis
Electromyography measures the electrical activity of muscles and the nerve signals that drive them. In MG, specific EMG patterns reveal the characteristic failure at the neuromuscular junction that underlies the disease. EMG is particularly useful when blood tests are negative or inconclusive.
Single-Fiber EMG and Repetitive Nerve Stimulation
Two specific electrodiagnostic techniques are used in MG diagnosis. Repetitive nerve stimulation (RNS) delivers a series of electrical pulses to a nerve and measures whether the muscle response decreases with each successive stimulus – a pattern called decremental response that is characteristic of MG. Single-fiber EMG (SFEMG) is one of the most sensitive tests used in MG evaluation, especially in mild, early, or antibody-negative cases. However, results must be interpreted in the context of the full clinical picture, because abnormal findings can occur in other conditions. SFEMG is typically performed at specialized neuromuscular centers and requires a clinician trained in the technique.
What to Do After a Myasthenia Gravis Diagnosis
Receiving a confirmed Myasthenia Gravis diagnosis answers one set of questions and immediately raises others. The next step is a conversation with a neuromuscular specialist about disease type, severity, antibody status, thymus evaluation, and the range of physician-guided management options. Because MG involves immune dysfunction at the neuromuscular junction, care planning should be individualized and medically supervised.
Treatment options for myasthenia gravis, including conventional medications, thymectomy, IVIG, and plasma exchange, are covered in detail on our myasthenia gravis treatment page, along with MaxWell Clinic’s integrative perspective on whole-body support for people navigating autoimmune and neuromuscular conditions.
Frequently Asked Questions About Myasthenia Gravis Diagnosis
How long does it take to get a myasthenia gravis diagnosis?
It varies considerably. Some patients receive a diagnosis within weeks of their first symptoms, particularly when eye symptoms are classic and AChR antibodies are positive. For others, the process takes months or years, especially when symptoms are intermittent, atypical, or when initial testing is negative. In some studies, more than a quarter of MG patients experience a diagnostic delay of over a year. If you have been evaluated for other conditions without resolution and MG fits your symptom pattern, asking about an MG antibody panel and a referral to a neuromuscular neurologist is a reasonable next step.
Can a blood test confirm myasthenia gravis?
A positive AChR antibody test in a patient with characteristic symptoms strongly supports the diagnosis of MG and may be enough to confirm it in many cases. However, blood tests alone cannot confirm MG in every case. Some patients are seronegative on standard panels, and ocular MG has a higher rate of false-negative antibody results. A negative blood test does not rule out MG – it means additional evaluation, such as EMG or specialist assessment, may be needed.
Can myasthenia gravis be misdiagnosed?
Yes. MG can be difficult to recognize because it may resemble other neurologic, eye, thyroid, respiratory, or fatigue-related conditions. The fluctuating nature of symptoms and the absence of typical sensory symptoms can make it easy to attribute the presentation to other, more commonly encountered conditions. Patients who have received diagnoses that did not fully explain their symptoms, or whose condition has not responded to treatment as expected, should consider whether MG has been adequately evaluated.
Do I need to see a specialist to be diagnosed with MG?
A formal MG diagnosis requires neurological evaluation, and ideally evaluation by a neuromuscular specialist. While a primary care physician or general neurologist can initiate the antibody workup, interpreting the full picture – including seronegative cases, equivocal EMG results, and the appropriate classification of disease type and severity – is best done by someone with specific expertise in neuromuscular disease. If access to a specialist is limited, academic medical centers and tertiary neurology practices typically have dedicated neuromuscular clinics.
What happens after myasthenia gravis is confirmed?
Once MG is confirmed, the next step is determining the type and extent of the disease – which antibodies are present, whether the thymus is abnormal, and how severe the weakness is. This information helps shape the care plan. Your treating neurologist will typically order a chest CT or MRI to evaluate the thymus and will then discuss management options, which may range from first-line medications to more advanced interventions depending on disease severity and patient goals.
Once MG is confirmed, the next step is working with a neuromuscular specialist to build an individualized care plan. If you want to learn whether MaxWell Clinic’s integrative, physician-guided services may complement your existing neurological care, call (615) 370-0091 to speak with our team. Your antibody status, thymus findings, symptom severity, overall health, and current treatment plan will help determine what comes next after a myasthenia gravis diagnosis.